“Nature’s Ozempic” is a marketing phrase, not a clinical category. No over-the-counter supplement, food, or drink has been shown to match the GLP-1 receptor agonist activity, appetite suppression, or weight-loss outcomes produced by prescription semaglutide. A handful of natural compounds may produce modest glucose-lowering effects through unrelated mechanisms.
Where the Phrase Came From
Social media accounts began labeling berberine “nature’s Ozempic” in 2023, shortly after semaglutide-based weight-loss drugs went viral. The phrase has since been applied to glucomannan fiber, oat beta-glucan, apple cider vinegar, chromium picolinate, bitter melon, and various branded supplement blends. The common pitch: a natural compound that mimics what Ozempic does without an injection or prescription.
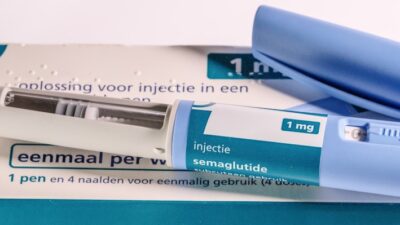
The pitch is misleading. Ozempic (semaglutide) is a synthetic peptide that binds and activates the GLP-1 receptor for roughly a week per dose. No food or supplement does this.
What Ozempic Actually Does
Semaglutide is a glucagon-like peptide-1 (GLP-1) receptor agonist. It slows gastric emptying, increases insulin secretion in response to meals, suppresses glucagon, and acts on hypothalamic appetite centers to reduce hunger. In the STEP trials, weekly semaglutide produced average weight loss of 12 to 15 percent of body weight over 68 weeks, with concurrent reductions in A1C of roughly 1.5 to 1.8 percentage points in people with type 2 diabetes.
For context on what those numbers mean, see our overview of A1C levels and the broader prediabetes treatment options.
The Most-Hyped “Natural” Candidates
Berberine
Berberine is a plant alkaloid extracted from goldenseal, barberry, and Oregon grape. It activates AMP-activated protein kinase (AMPK), the same energy-sensing enzyme metformin influences. A 2008 trial by Yin and colleagues reported A1C reductions of roughly 0.9 percentage points over three months at 1,500 mg per day, comparable to metformin in that small study. Subsequent meta-analyses report more modest and inconsistent effects. It does not act on the GLP-1 receptor.
Soluble Fiber (Glucomannan, Psyllium, Beta-Glucan)
Soluble fibers form a viscous gel in the stomach, slowing gastric emptying and blunting post-meal glucose spikes. Psyllium can lower fasting glucose modestly and improve LDL cholesterol. Glucomannan can produce small short-term weight loss, likely through satiety. None of these mimic the central appetite suppression Ozempic produces.
Protein
High-protein meals trigger short-lived endogenous GLP-1 release from L cells in the gut. The peptide is broken down within minutes by DPP-4, so the effect on circulating glucose is fleeting. Ozempic’s molecular structure resists DPP-4, which is why a weekly dose works.
Apple Cider Vinegar, Cinnamon, Bitter Melon, Chromium
Each has a thin evidence base for small reductions in fasting or post-meal glucose. None produce clinically meaningful weight loss in controlled trials. None act on GLP-1 receptors.
Side-by-Side Comparison
| Agent | Mechanism | Typical A1C Effect | Weight Loss |
|---|---|---|---|
| Semaglutide (Ozempic) | GLP-1 receptor agonist | 1.5 to 1.8 points | 12 to 15 percent |
| Berberine 1,500 mg/day | AMPK activation | 0.5 to 0.9 points (variable) | 1 to 3 percent |
| Psyllium 10 g/day | Viscous fiber, slows absorption | 0.2 to 0.5 points | Minimal |
| Glucomannan 3 g/day | Satiety via gel formation | Minimal | 2 to 4 pounds short-term |
| Apple cider vinegar | Delayed gastric emptying (small) | Minimal | Minimal |
What Marketing Often Leaves Out
- Supplements are regulated as food, not drugs. Label-claim accuracy and ingredient purity vary widely.
- Berberine has a low oral bioavailability and frequently causes nausea, diarrhea, and constipation.
- Berberine inhibits CYP3A4, which can raise levels of statins, calcium-channel blockers, and some chemotherapy drugs.
- Glucomannan must be taken with at least 8 ounces of water; capsules have caused esophageal obstruction.
- “Stacked” supplement blends often contain doses too low to match the trial-level effects they advertise.
What May Genuinely Help
If your goal is steadier glucose without a prescription, the highest-yield interventions remain dietary fiber, protein at every meal, post-meal walking, and weight loss through sustained calorie balance. Reviewing the diet and nutrition approach and learning the basics of prediabetes detection typically delivers more than any single capsule.
When to Talk to a Clinician
If you are considering a “natural Ozempic” because a prescription option feels out of reach, raise it with your primary-care clinician. Generic metformin is inexpensive and well studied, and several GLP-1 receptor agonists are now covered by insurance plans for prediabetes-adjacent indications such as obesity. A clinician can also flag interactions between supplements and medications you already take.
The Bottom Line
“Nature’s Ozempic” sells better than it works. Berberine, fiber, and protein each have a real but limited role in glucose management, and none replicate semaglutide’s pharmacology. Use them as adjuncts to evidence-based diet and exercise, not as a substitute for medical care. If a product promises Ozempic-level results, the marketing has outrun the data.